
At the bedside · Nursing practice
The medicine trolley is ready, a relative is waiting by the door, and another patient has called for help. Then someone looks up from the bed and says, “Nurse, I’m scared.” What you say next matters.
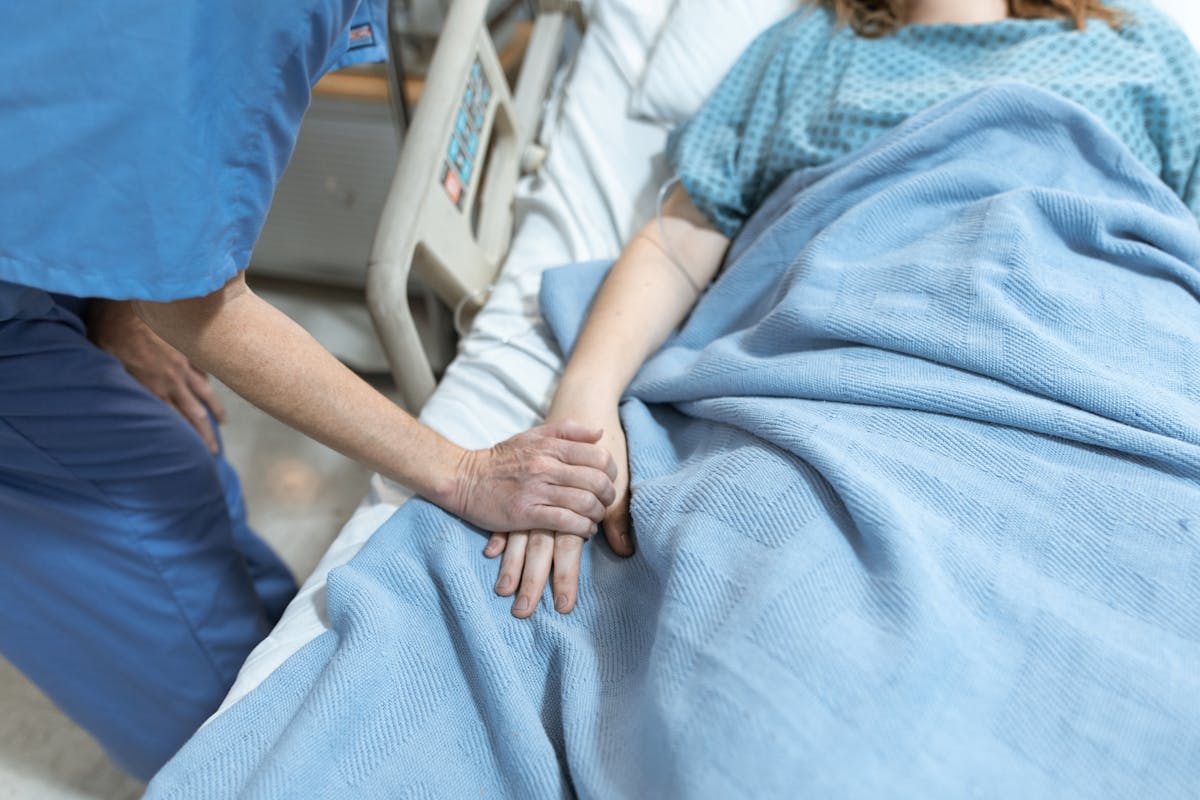
You do not need a perfect speech. You need to find out what the person is frightened of, recognise anything that needs urgent attention, and explain the next step honestly. This article offers practical wording for those ordinary bedside moments when a patient needs more than instructions.
1. Make room for the first answer
“What is worrying you most right now?” gives the patient somewhere to begin. The answer may be pain, a procedure, a possible diagnosis, money, or the children waiting at home. Asking before explaining helps you avoid delivering a long answer to a question the patient never asked.
Where it is safe to pause, turn towards the person and let them finish. AHRQ recommends open questions, attentive listening, and clear, everyday language. These are useful habits when the ward feels hurried and your attention is being pulled in several directions. [1]
“You have mentioned the operation twice. Is it the procedure itself that worries you, or what might happen afterwards?”
This is an example of a follow-up question, not a script to repeat word for word. Use the patient’s own concern as your starting point. If they say, “I don’t know,” try, “What has been on your mind since you arrived?” Give them a moment. Silence can be awkward for the nurse without being unhelpful to the patient.
If fear comes with a new symptom or a sudden change in condition, assess promptly and use your facility’s escalation procedure. Reassurance must not delay urgent help. Work within your competence and involve the appropriate clinician when needed. [3]
2. Offer reassurance you can stand behind
It is tempting to say, “Everything will be fine.” But you may not know the result of the test, how the patient will recover, or when a clinician will arrive. A more useful promise is about something you can actually do.
- When the outcome is uncertain: “I don’t have that answer yet. I can explain what is planned next and help you get your questions to the team.”
- When the patient expects pain: “Tell me what you are worried about. We can discuss the pain-relief plan with the team before we begin.”
- When there has been a delay: “I know you have been waiting. I will check what is happening and update you with what I find out.”
Only offer an update or return time you can reasonably meet. If your circumstances change, arrange for a colleague to follow up or explain the delay. An honest update may still disappoint someone, but it does not leave them trying to guess whether they have been forgotten.
3. Explain the next step, not the whole admission
A patient who is frightened may have one immediate question: “What are you about to do to me?” Start there. AHRQ advises prioritising a small number of important points and using plain language. [1] For example, “I’m going to check your blood pressure now” is easier to follow than a hurried list of observations and abbreviations.
Imagine preparing someone for a routine blood sample. You might say, “A blood sample has been requested. I’ll explain how we take it, and you can ask questions before we start.” Follow the actual care plan and your consent procedures; a friendly explanation does not replace informed consent.
Tell the patient when you need to check a detail. “Let me confirm that before I advise you” is a professional response. Guessing to keep the conversation moving can create a problem that another nurse then has to untangle.
Ask which language the person prefers. Where language support is needed, arrange a qualified interpreter through the available service rather than relying on limited language skills or assuming a relative can interpret accurately. AHRQ specifically recommends qualified interpretation. [1]

4. A nod does not tell you what was understood
Teach-back asks the patient to describe the important information in their own words. AHRQ presents it as a check on the explanation, not an examination of the patient. If something is unclear, explain it differently and check again. [2]
“We have covered several things. So I can check that I explained them clearly, how will you follow this plan when you get home?”
For a practical skill, ask for a demonstration where appropriate. Keep the question relevant to the instruction you have just given. A person does not have to repeat your exact wording to show that they understand, and written instructions can remain in front of them. [2]
Consider the difference between these two endings to a conversation: “Any questions? Good,” and “Which part would you like us to go over again?” The second makes it easier to admit uncertainty. It also gives you a specific place to restart rather than repeating the entire explanation more loudly.
5. Include family without losing the patient’s voice
A relative may arrive with useful questions or simply want to sit nearby. Ask the patient whom they want involved and what they are comfortable discussing. Maintain privacy, follow local consent and capacity requirements, and share information appropriately. The UK NMC Code emphasises dignity, confidentiality and respect for individual choices. [3]
A useful opening is, “Would you like us to discuss this together, or would you prefer a few minutes privately first?” Address the patient directly even when the relative is doing most of the talking. Where a family member has raised a question, return to the patient with, “Is that also what you wanted to ask?”
In a shared ward, look at the setting before starting a sensitive conversation. A lowered voice and a curtain may help, but they do not make a space soundproof. If the discussion can safely wait for a more private place, arrange one.
6. Be realistic about the shift you are working
There will be moments when you cannot sit down for a long conversation. A practical response is to acknowledge the concern, identify whether it needs immediate action, and make a clear arrangement for follow-up.
“I can hear that you are worried. Tell me the most urgent concern first, so I can work out what help you need now.”
If another emergency requires your attention, involve a colleague when possible. Avoid a vague “later” that leaves the patient watching the door. Record relevant concerns, what action was taken, and any follow-up still needed; this supports continuity when another nurse takes over. [3]
After the shift, choose one conversation to reflect on. Where did you interrupt? What question helped? Was there a promise you could not keep? One specific change is easier to practise on the next shift than a general instruction to “communicate better.”
7. A short scenario to practise with a colleague
The following is a fictional teaching example, not a report about an actual patient.
A patient awaiting a planned procedure repeatedly asks whether the clinician is coming. When approached, the patient says, “I’m scared. Nobody has told me anything.” A rushed answer would be, “Just relax; they will come.” Try this instead:
“Waiting without an update is upsetting. What would you most like to know? I can tell you what is confirmed in the plan, and I will ask the team about anything I cannot answer.”
Let your colleague play the patient and give an unexpected answer: perhaps the real concern is whether someone has informed a family member. Practise responding to that answer instead of returning to your prepared explanation. Then swap roles. Notice whether the conversation ends with a clear next step.
Before you leave the bedside
- Do I know the patient’s main concern?
- Have I acted on anything needing assessment or escalation?
- Have I explained the next step in words the patient can follow?
- Have I checked understanding where instructions were given?
- Does the patient know how to seek help, and who will follow up?
A good bedside conversation often ends quite simply: the patient has been heard, an important question has been answered, and the next action is clear. You may not remove every fear. You can make sure the person does not have to carry that fear without knowing how to ask for help.
Read our practical SBAR communication guide, explore clinical skills articles, or visit the Mini Nurses practice centre.
Sources and further reading
- Agency for Healthcare Research and Quality. Communicate Clearly: Tool 4. Health Literacy Universal Precautions Toolkit, 3rd edition; reviewed April 2024.
- Agency for Healthcare Research and Quality. Use the Teach-Back Method: Tool 5. Reviewed April 2024.
- Nursing and Midwifery Council, United Kingdom. The Code, particularly sections 2, 4, 5, 10 and 13. Used here as an international professional reference; it does not replace Nigerian professional requirements or your facility’s policies.
Educational article for nurses and nursing students. Apply your local clinical protocols, professional scope and escalation procedures. Conversation examples are original teaching illustrations. Both photographs are by RDNE Stock project, published on Pexels in December 2020 and used under the Pexels licence; no endorsement by the people pictured is implied.